

Vernal keratoconjunctivitis is a chronic allergic eye disease commonly seen in younger people.
It is seen especially often in junior high and high school boys who play sports.
It often develops in students who play sports such as soccer, baseball (for example, players aiming for Koshien), and judo.
Severe Allergic Conjunctivitis (Vernal Keratoconjunctivitis)
Vernal keratoconjunctivitis:Typical patients and characteristic symptoms
Vernal keratoconjunctivitis is a chronic disease, and more than 60% of patients have repeated relapses and remissions throughout the year.
Among patients aged 20 or younger, it is reported to be 3.2 times more common in males than in females.1。
After age 20, the male-to-female ratio seems to become equal.
Fortunately, vernal keratoconjunctivitis is a disease that more often “gets better” (a disease with a good prognosis).
Vernal keratoconjunctivitis:Main symptoms and features
The severely inflamed “conjunctiva” is always in contact with the cornea (the black of the eye).
If corneal damage from long-standing inflammation develops, it can leave “after-effects” of reduced vision.
That is why early diagnosis and appropriate management are needed.
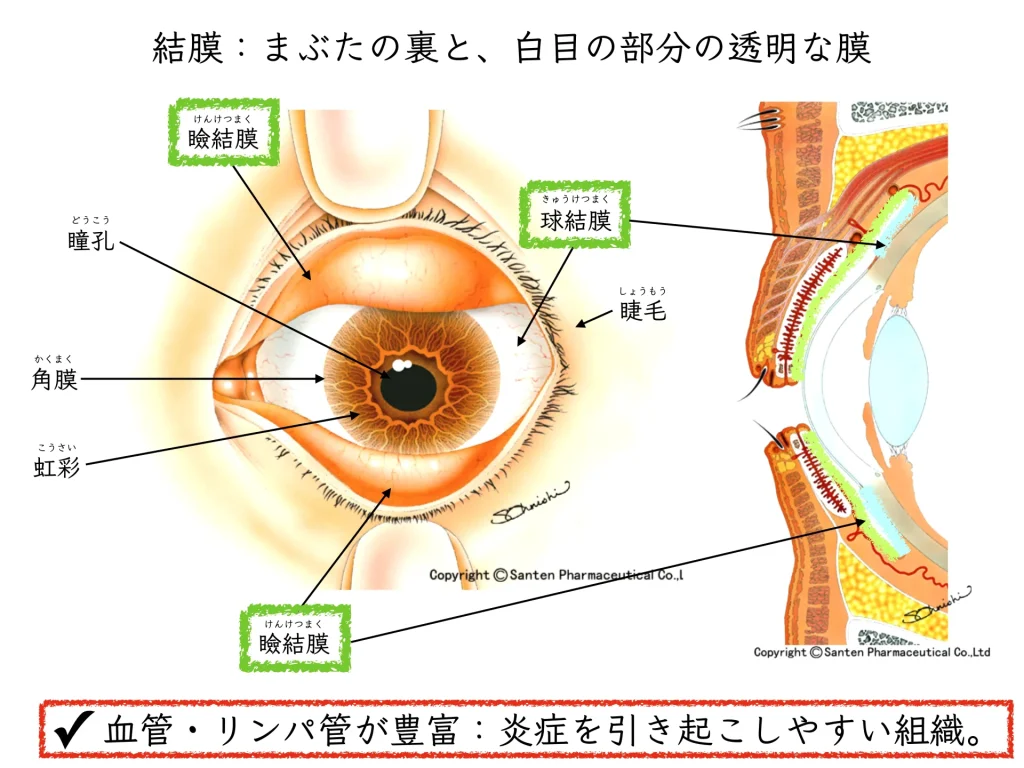
In vernal keratoconjunctivitis,
the “conjunctiva” on the inside of the upper eyelid mainly becomes severely inflamed.
That conjunctiva takes on a “cobblestone” appearance and produces a lot of discharge: “giant papillary proliferation”
It causes a variety of symptoms, such as intense itching, pain, a foreign-body sensation, and photophobia (light sensitivity).
Vernal keratoconjunctivitis:Complications and points to watch
The most important thing to watch for in vernal keratoconjunctivitis is the effect of long-term inflammation on the cornea.
Because the conjunctiva is always in contact with the cornea, there is a risk of:
- Corneal erosion
- Development of a condition called a shield ulcer
- Reduced vision if treatment is delayed
The “cytokines” that make up much of the discharge damage the black of the eye (cornea) and create erosions.
Corneal damage influenced by “Th2 cytokines,” which are involved in humoral immunity (allergy)
In vernal keratoconjunctivitis, it is important to observe the condition of the cornea (the black of the eye) closely.
The “Th2” group among T lymphocytes does harm and worsens the inflammation2。
and can affect the cornea that touches the conjunctiva.
This is the condition called a “shield ulcer.”
Once an erosion forms, the cornea can become cloudy, which can affect vision for life.
Vernal keratoconjunctivitis: treatment
The basis of treatment is to suppress inflammation while keeping the eye tissue transparent.
That is why, after making the diagnosis,how early we can suppress the inflammationis very important.
(That is why I sometimes ask you to keep coming to the eye clinic for a while.)
The basis of treatment is steroids, aiming to strongly suppress inflammation overall.
○ Rinderon® eye drops
○ Fluorometholone (Flumetholon®) eye drops
○ Steroid suspension (Kenacort®) injection under the eyelid (subtarsal)
We start with stronger treatment (frequency and degree) and gradually reduce the suppression of inflammation.3。
During treatment we always monitoreye pressure.
The problem that arises during steroid treatment is steroid-induced glaucoma.
Children and young people tend to have a strong rise in eye pressure, and treatment can be very difficult.
Immunosuppressants, which became covered by insurance in 2010, can also be used.
Because they are large molecules, they have almost no systemic side effects.
○ 0.1% tacrolimus eye drops (Talymus® ophthalmic suspension)
○ 0.1% cyclosporine eye drops (Papilock Mini® ophthalmic solution)
By using an immunosuppressant,
we suppress the function of the T cells that drive allergic inflammation.
While watching for infection,
we proceed with treatment, considering the immune status of the T cells (lymphocytes).
References
1. Bonini, Stefano, Bonini, Sergio, Lambiase, A., Marchi, S., Pasqualetti, P., Zuccaro, O., Rama, P., Magrini, L., Juhas, T., Bucci, M.G., 2000. Vernal keratoconjunctivitis revisited. Ophthalmology 107, 1157–1163. https://doi.org/10.1016/S0161-6420(00)00092-0
2. Bonini, S., Coassin, M., Aronni, S., Lambiase, A., 2004. Vernal keratoconjunctivitis. Eye 18, 345–351. https://doi.org/10.1038/sj.eye.6700675
3. Kumar, S., 2009. Vernal keratoconjunctivitis: a major review. Acta Ophthalmologica 87, 133–147. https://doi.org/10.1111/j.1755-3768.2008.01347.x























