
“Which myopia control treatment works best?”
This is something parents often say when they consult us about myopia treatment.
There is no single “best” answer.
The right choice changes with the child’s pattern of axial length growth, age, lifestyle and the family’s values. At Takeru Eye Clinic, rather than the doctor deciding one-sidedly “please go with this,” we value the process of thinking it through and choosing together with the family.
In this article I describe that thinking and how we actually carry it out in the clinic.
It is an introduction to the idea of Shared Decision Making (SDM).
We have introduced a new device (July 17, 2026)
We have switched to the “OA-1,” a new measuring device that shows “how many millimeters axial length grows per year (the speed of progression)” as a slope and lets us compare with percentile curves for Japanese children (ages 4–15).
First, let’s sort out what we understand about myopia
Before getting into myopia control treatment, let’s stop and check once.
Parents often say things like “wearing glasses makes your eyes worse,” “myopia can’t be helped,” and “contact lenses are too early.” Many have believed this for years.
In fact, these had no strong scientific basis.
Over the past 10–15 years, thinking about children’s myopia has changed greatly. The very idea of “myopia control” is a relatively new concept. Until then, most lifestyle guidance was based on impressions and habits.
And now we are in an era in which there are multiple treatments that can actually slow the progression of myopia.
At the start of every consultation, I always share this. If I began explaining treatment while leaving decades of assumptions as they are, it would be brushed off as “that’s a bit exaggerated.” So we first sort out understanding, and then choose together.
Myopia management treatment: why “decide together”?
Once myopia management treatment begins, it continues for several years. Orthokeratology requires lens care every night, eye drops require daily continuation, and myopia control glasses require wearing for 12 hours or more a day.
No matter how effective a treatment is, it is meaningless if it cannot be continued. And how easy it is to continue depends greatly on the sense of conviction that “we chose it ourselves.”
A Taiwanese study of 314 parents, published in 2025 inBMC Ophthalmology, showed that in myopia management, SDM was the factor that most strongly predicted “freedom from regret.” How the choice was made influenced parents’ regret and satisfaction more strongly than the type of treatment (atropine or orthokeratology)¹.
This way of thinking in medicine is called SDM (Shared Decision Making).
“Myopia management treatment is a gift to the child’s future. Choosing with conviction lasts longer than choosing in a hurry.”
— Dr. Kurachi (8th Annual Meeting of the Japanese Society of Myopia, June 2026)
After hearing a lecture at the 2026 Society of Myopia meeting, I learned this idea of “SDM” anew.
At Takeru Eye Clinic, we have organized how we explain things along the SDM framework.
Confirming “whether treatment is needed”
Before explaining the options, we first confirm whether “this is a state that needs intervention (treatment) right now.” We refer to the following criteria.
If any one of these applies, we explain the treatment options. Even if none apply, we keep watching while measuring axial length every 3 months.
If amblyopia is present, amblyopia treatment takes priority over myopia management. Myopia arising from prematurity and pathologic myopia differ in pathology from ordinary myopia management and need individual handling. I will explain in detail at the consultation.
Learning the options for myopia control: six choices including “doing nothing”
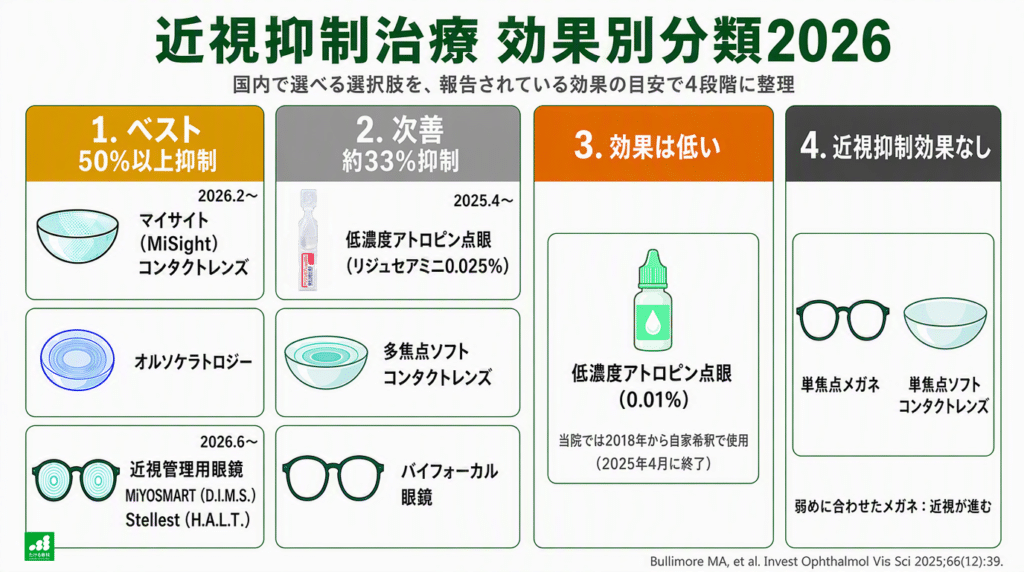
There are 5 treatments we currently offer. Adding “observation (doing nothing)” to these gives the 6 options in all.
Every treatment has pros and cons, and suits some children and families better than others. We also tell you about treatments we do not offer (such as RLRL red-light therapy) and present them side by side neutrally (a policy based on the international quality standard IPDAS*³).
- Orthokeratology (OrthoK): Special hard lenses are worn during sleep, and you spend the day without glasses or contact lenses. The effect in slowing the growth of axial length is said to be up to about 50%⁷. It is often chosen by children who do sports or swimming.
- Low-concentration atropine eye drops (Ryjusea® Mini 0.025%): Only one eye drop a day. It takes the least effort and can be started at a young age. First approved in Japan in April 2025.
- MiSight® 1 day (daily-replacement soft contact lens): The world’s first soft contact lens approved for myopia control. It has 7 years of evidence, and a 59% suppression of refractive progression has been reported⁶.
- Myopia control glasses (MiYOSMART®, Stellest®): Just wear glasses. Because nothing touches the eye, this is the lowest-barrier option. We began offering them at our clinic in June 2026.
- OrthoK + atropine combination: The combination said to be the most effective at present. We consider it when both parents have high myopia and the child is thought to be at high risk.
- Observation (doing nothing): This includes wearing ordinary glasses. No treatment is given, and axial length is checked regularly. This is also an important option.
For the effect, effort, cost and suitability by age of each treatment, please see the following materials.
Randomized controlled trial (RCT) data and the literature for each treatment are explained in detail in a separate article.
*International Patient Decision Aid Standards (IPDAS)
https://decisionaid.ohri.ca/ipdas/
Your choice changes depending on what matters to you
Even when axial length grows at the same pace, different families have different priorities. Some say “I want the one that works best,” others “let’s start with something that takes little effort.” Both are right.
Try sorting out your family’s wishes along the following axes.
How we “decide together” at Takeru Eye Clinic
We proceed with explanation and choice in 3 steps, dividing roles betweencertified orthoptists (CO) and the doctor. You do not need to decide everything at the first visit. The flow is that you decide from the second visit on, once you are satisfied.


STEP 1 | Learn that options exist (orthoptist, first visit)
At the time of the preliminary tests, after a lead-in of “the doctor will also talk with you in detail,” we lightly introduce that thinking about myopia has recently changed. We present it not to push treatment but as a chance to learn that there are options. We hand you a pamphlet explaining myopia.
STEP 2 | Compare and sort the options (orthoptist, first visit)
We hand you the axial length results together with a printout of the percentile curve. At present we measure with the AL-Scan (Nidek) and evaluate with Tideman’s global standard curve. After the OA-1 (Tomey) is introduced, we plan to move to the Japanese percentile curve. Using a treatment comparison sheet, we explain the 6 options side by side. We always mention “doing nothing (observation)” as well.
STEP 3 | The doctor gives an overall explanation and you take it home (doctor, first visit)
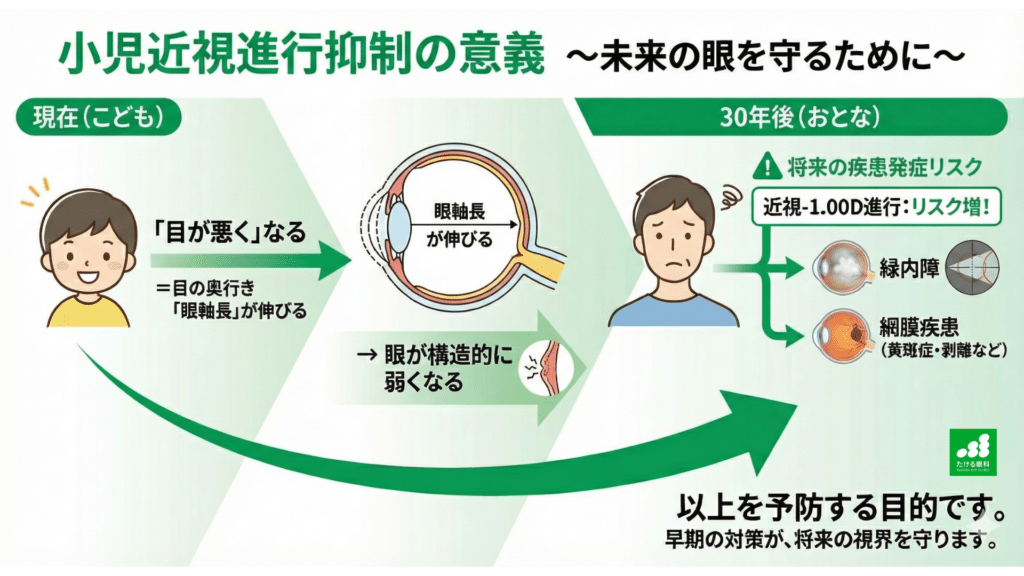
With one picture, we explain once more that “the common sense about myopia we used to hold has changed.” We also give you a QR code (content showing that each step of myopia progression raises future disease risk).
At the first visit, we limit it to the explanation above. Please read it slowly with your family and the “key persons,” and once you are satisfied, come back and book the next examination together.
From the second visit | Questionnaire → orthoptist reconfirmation → doctor’s Decision Talk → start of treatment
At visits from the second onward, we use a questionnaire (filled in yourself, or confirmed verbally by the orthoptist). It has 5–6 questions such as “Did you receive sufficient explanation?”, “Have cost and effort been sorted out?” and “Has the family reached agreement?”
The orthoptist reconfirms based on the questionnaire results, and the doctor talks only about the points you are “still unsure about.” The doctor’s consultation is not long. But so that it can still explain enough, we secure time with the orthoptist first.
If everyone in the family is satisfied, we start treatment. If you are still unsure, you are welcome to keep taking it home. It is fine to contact us 1–2 weeks later. If the child is not yet keen, let’s wait a little longer.
Guide after starting myopia control treatment
Starting treatment is not the end. We measure axial length every 3 months and confirm the speed of progression with numbers.
We believe that being able to feel the effect in numbers leads to long-term continuation.
For parents in the myopia management program, we have independently developed and offer the “Myopia Management Report” app, which lets you check changes in axial length on your smartphone. If you enter the axial length measured at each visit, you can immediately see the trend graph, a percentile comparison with international standard data (BHVI / Donovan 2012), and a 3-level display of the speed of progression (green / yellow / red) (the display is for reference only; evaluation is done at the consultation). Data is stored only on your smartphone and is not sent to a server. It also supports managing siblings.
→ Myopia Management Report app
Summary
- Myopia is a progressive change in which “the eyeball lengthens.” We can now slow its progression with treatment.
- There is no single correct answer to treatment. The answer that suits each child differs with the child’s situation and the family’s values.
- Based on SDM, Takeru Eye Clinic values the process of presenting 6 options neutrally and then deciding together.
- Securing 2 hours or more of outdoor activity a day is, alongside myopia control treatment, the foundation of a healthy lifestyle.
- After treatment as well, we measure axial length every 3 months and continue while confirming the effect with numbers.
- You do not need to decide on the day of the first visit. Take it home, and decide once your family is satisfied. It is not too late even then.
Together with the visual acuity test,
measuring “axial length” is the most important thing.
The first visit is covered by insurance. No appointment is necessary.
References
- Hung LL, Sun CC, Chang LC, Liao LL. Factors influencing shared decision-making and decision regret in parents of children undergoing myopia control within one year. BMC Ophthalmol. 2025;25(1):609. doi:10.1186/s12886-025-04433-w https://pubmed.ncbi.nlm.nih.gov/41174703/
- Stacey D, Lewis KB, Smith M, et al. Decision aids for people facing health treatment or screening decisions. Cochrane Database Syst Rev. 2024;1:CD001431. doi:10.1002/14651858.CD001431.pub6 https://pubmed.ncbi.nlm.nih.gov/38284415/
- Stacey D, Volk RJ. The International Patient Decision Aid Standards (IPDAS) Collaboration: Evidence Update 2.0. Med Decis Making. 2021;41(7):729-733. doi:10.1177/0272989X211035681 https://pubmed.ncbi.nlm.nih.gov/34416841/
- Bullimore MA, Saunders KJ, Baraas RC, et al. IMI—Interventions for Controlling Myopia Onset and Progression 2025. Invest Ophthalmol Vis Sci. 2025;66(12):39. doi:10.1167/iovs.66.12.39 https://pubmed.ncbi.nlm.nih.gov/40960225/
- Bullimore MA, Brennan NA. Myopia control: why each diopter matters. Optom Vis Sci. 2019;96(6):463-465. doi:10.1097/OPX.0000000000001367 https://pubmed.ncbi.nlm.nih.gov/31116165/
- Chamberlain P, Peixoto-de-Matos SC, Logan NS, et al. A 3-year Randomized Clinical Trial of MiSight Lenses for Myopia Control. Optom Vis Sci. 2019;96(8):556-567. doi:10.1097/OPX.0000000000001410 https://pubmed.ncbi.nlm.nih.gov/31343513/ Chamberlain P, Bradley A, Arumugam B, et al. Long-term Effect of Dual-focus Contact Lenses on Myopia Progression in Children: A 6-year Multicenter Clinical Trial. Optom Vis Sci. 2022;99(3):204-212. doi:10.1097/OPX.0000000000001873 https://pubmed.ncbi.nlm.nih.gov/35086120/
- VanderVeen DK, Kraker RT, Pineles SL, et al. Use of Orthokeratology for the Prevention of Myopic Progression in Children: A Report by the American Academy of Ophthalmology. Ophthalmology. 2019;126(4):623-636. doi:10.1016/j.ophtha.2018.11.026 https://pubmed.ncbi.nlm.nih.gov/30476518/























